What Yonsei's Metabolic MRI Installation Has to Prove
A university project gets a deployment window
The RESQ consortium plans to install NVision's POLARIS platform at Yonsei University in early 2027. Backed by €2,572,500 in Horizon Europe funding, the three-year program joins NVision, Yonsei University, Ulm University, and Tesla Dynamic Coils. Together they are building a metabolic MRI installation for higher-resolution research on brain metastases. The public project record assigns concrete work: reproducible parahydrogen generation and storage, tailored radiofrequency pulses, compressed sensing, machine learning, and dedicated dual-tuned brain coils. These details turn a broad quantum-health ambition into a dated engineering program with named owners.
The scanner is only one part of the workflow
Hyperpolarization can strengthen the MRI signal from selected metabolic agents for a limited period, allowing researchers to study what tissue is doing alongside its anatomy. That advantage can disappear if gas preparation, sample transfer, coil performance, pulse design, or image reconstruction varies. RESQ therefore has to integrate chemistry, hardware, software, scanner time, and operating procedure. Its stated goal of doubling spatial resolution is a consortium target. The current public record does not report a completed Yonsei installation, a disease-model result, a patient study, diagnostic accuracy, or a change in treatment.
Preclinical work is the next meaningful test
Yonsei is expected to validate the workflow using preclinical brain metastasis models. That stage can show whether the complete system produces stable metabolic maps in biologically relevant models and whether smaller lesions become more visible. It cannot yet establish performance in patients. Quentir reads RESQ as a quantum-sensing implementation program at TRL 4 of 9: the underlying hyperpolarization platform operates in research settings, while the new disease-specific workflow still awaits installation and integrated preclinical validation. The decisive question for the project period ending in April 2029 is whether preparation, acquisition, coil behavior, and reconstructed images can be reproduced beyond one expert site. A portable workflow would move quantum sensing closer to useful medical infrastructure; a result dependent on one installation would leave clinical translation much farther away.
The MRI Implication of a Single Copper-Oxide Plane
The result is one atomic plane
A team led by researchers at Fudan University and the University of Science and Technology of China has fabricated a single-layer cuprate containing one superconducting copper-oxide plane. Published in Nature on August 12, the experiment reduces Bi-2201 to its ultimate two-dimensional limit. The monolayer retained superconductivity, although its optimal transition temperature was about ten percent lower than in thicker material. Fine control of oxygen content then let the researchers follow the sample from an insulating state, through an anomalous metallic regime, and into superconductivity. This is a basic-physics achievement built on delicate fabrication and a laboratory instrument designed for precise in-situ tuning.
The medical relevance begins with the magnet
MRI depends on a strong, stable magnetic field to align protons in the body before radiofrequency pulses and sensors turn their response into anatomical images. That creates an MRI materials pathway for this research, but the connection sits far upstream. The paper reports no magnet winding, imaging coil, scanner prototype, patient study, or medical-device test. Its contribution is a cleaner experimental platform for understanding how high-temperature superconductivity changes when the active material is reduced to one copper-oxide plane.
The distance to care remains useful to measure
A hospital magnet requires far more than a superconducting transition. Engineers need scalable conductors, high current under strong fields, reliable joints, mechanical strength, controlled cooling, quench protection, field homogeneity, and compatibility with a complete scanner. The new monolayer does not answer those engineering questions. It helps make the earlier materials questions more exact. Quentir reads the result as a sensing story at the laboratory-materials stage: credible MRI relevance through superconducting magnet science, paired with a clear boundary around present readiness. The next meaningful step would connect the one-plane physics to a thicker, manufacturable material with measured current or field performance.

A Paid Quantum Drug Project Meets a Four-Stage Validation Ladder
The next calculation became funded work
China Securities Journal reported on August 14 that Shenzhen Jingtong Life Science tested Boson Quantum's approach on a drug-target structure problem in June and moved to a paid quantum drug-discovery engagement in July. The client named two difficult tasks: finding the precise binding conformation of a drug-target complex and calculating its energy after binding. It also reported an advantage in conformation search. The work now covers new molecules associated with healthy aging. The article says drug-related intellectual property would be jointly owned if the project succeeds, while software and algorithm rights would remain with Boson. The account is commercially meaningful because a buyer has funded a defined computational problem, yet the public article provides no molecule list, hardware configuration, classical baseline, runtime, success metric, or laboratory confirmation.
The same report sets a demanding standard
GuoDun Quantum executive Wang Zhehui supplied a four-stage validation ladder in the same article. It begins with benchmark advantage and initial industry validation on real quantum hardware. The decisive stages are superiority to classical algorithms under equal conditions and reproducible business outcomes. The engagement is commercially concrete, but the disclosed record cannot yet assign it a validation rung because real-hardware use and a controlled comparison remain undisclosed. Funded work may support learning, access, feasibility, or method development. It establishes customer demand without settling the scientific comparison.
The medical handoff remains ahead
Quantum computation would sit near the beginning of drug development. It may help decide which molecules deserve synthesis and testing, though it cannot establish safety, dosage, biological effect, or clinical benefit. Quentir reads the account as a useful commercial milestone with a built-in limit. The reported planned IP allocation recognizes a reusable computational method on one side and, if the project succeeds, a medicine that must survive laboratory, preclinical, and clinical work on the other. Paid work has started before a reproducible pharmaceutical result. The next public milestone that changes the judgment would connect an equal-condition computational comparison to a wet-lab result that another team can understand and repeat.
A Photosensitizer Has Two Jobs Before Quantum Computing Helps
Two molecular jobs define the target
A light-activated cancer drug must absorb light in a useful therapeutic window and turn that energy into chemistry that damages a tumor. Xanadu and the University of Alberta announced on August 13 that they will develop quantum algorithms for photosensitizer design. The research partnership follows a December 2025 preprint that specifies both desired outputs: cumulative absorption and intersystem crossing rates linked to reactive-oxygen production. The paper applies proposed fault-tolerant algorithms to BODIPY derivatives, including substitutions that are difficult for standard computational chemistry. This is a sharply defined pharmaceutical calculation, although the announcement reports no new molecular result, hardware run, candidate compound, or development timeline.
The resource estimate belongs to a future machine
The preprint studies active spaces of 11 to 45 spatial orbitals and estimates a need for roughly 180 to 350 logical qubits. Logical qubits are encoded across physical qubits and require error-correction overhead, so that estimate cannot be compared directly with headline physical-qubit counts. Xanadu therefore places the work in fault-tolerant quantum computing, while Professor Alex Brown contributes expertise in photodynamic therapy chemistry and the excited-state processes that classical methods struggle to capture. The partnership joins an algorithm team and a chemistry group around a named failure point in simulation. Its technology readiness remains early because no calculation has yet been reported on suitable hardware or checked against laboratory measurements.
Clinical usefulness still runs through the laboratory
Photodynamic therapy is an established local treatment for selected cancers and precancers, but better photosensitizer calculations must still survive pharmacology, toxicology, formulation, delivery, and trials. A future quantum result would need comparison with measured spectra, photochemical rates, and strong classical baselines. Quentir reads the partnership as a disciplined research bet: the biomedical quantities are prespecified, the molecular class is named, and the resource assumptions are public. Progress will become legible when the workflow reproduces a known molecule's behavior and then ranks unfamiliar candidates well enough to save synthesis cycles.

A One-Number Test for the Brain's Signal Carriers
One number bounds what a brain signal can carry
A preprint posted to arXiv on August 11 gives the quantum-brain debate something it has lacked: a shared standard. Eran Kopel shows that spectral distinguishability alone bounds the labels a biological oscillator can carry by its quality factor, two pi times frequency times coherence time. The ceiling holds for any substrate and any mechanism, takes no position on quantum effects in biology, and can be computed from two published quantities. Collective vibrational modes, endogenous electromagnetic fields, microtubule excitations and oscillatory phase codes now face one arithmetic instead of four separate arguments.
A proposed cortical microwave field fails by every route
Applied to a recently proposed 30 gigahertz field inside cortical columns, the screen returns a quality factor of 0.19, a linewidth five times the carrier frequency. The rescue of a driven, spectrally narrow emitter requires a resonant cavity the model's own geometry forbids, and an independent metabolic-power bound is exceeded by five to nine orders of magnitude. Of eleven screened carriers, only the low-frequency neural rhythms pass. High-frequency molecular carriers fall to brevity, and the fragility argument the debate assumed proves unnecessary.
Braintech rides the rhythms that pass
Closed-loop EEG platforms already work in the frequency range the screen favors, portable designs keep maturing, and national programs are putting dates on commercial neurotechnology. Quentir reads the screen as inexpensive governance for an expensive decade: state the frequency, state the coherence time, and accept the ceiling they imply, with quantum sensing as the measurement arm being developed to pin those numbers down in living tissue.

Korea Moves Medical AI Oversight Upstream
Trust moves from one product to its maker
South Korea's Ministry of Food and Drug Safety has issued an 81-page guide for an organization-level medical AI certification. The assessment covers software quality, safety management, protection against electronic intrusion, and AI controls across the manufacturer. Applicants must provide manuals, procedures, development records, and material on transparency and explainability. Review combines document assessment with an on-site investigation. The result applies to the certified organizational unit for three years, giving MFDS a way to examine how a maker develops, tests, monitors, maintains, and changes AI software across more than one product. That continuity matters when several models share one development system.
Clinical learning can continue after authorization
For eligible standalone medical-device software, certification can support a real-world evaluation pathway. Some clinical-evaluation material may initially be replaced by product information and a real-world evaluation plan. The resulting report follows after authorization, within a period that can extend to three years, and MFDS must conduct an additional review before the authorization is extended. This can shorten the distance between development and clinical use, while moving some uncertainty into hospitals. Version history, post-deployment monitoring, incident channels, and the ability to detect performance drift become part of the safety system.
The certificate has a boundary
The guide requires clinical participation, AI risk management, red-team activity, software-component records, security responsibility, training-data governance, and monitoring in clinical settings. Those controls can support disciplined development. They do not prove that every model from an organization holding the recognition performs well for every patient population or workflow. Quentir reads Korea's framework as an exchange: regulatory flexibility for a demonstrably mature operating system, paired with continued product-specific scrutiny and later real-world review. The decisive test comes after certification, when a clinician questions an output, a hospital detects drift, or an update changes the model that patients encounter. Those local signals determine whether organization-level trust remains connected to the clinical reality of one population and software version.
A Korean Pharma Webinar Names the Quantum Workload
The announcement names the computing path
KPBMA's first AI drug-discovery webinar, focused on quantum computing, is scheduled for August 13. Tech42 reports that SDT plans to present a hybrid quantum computing stack built around its QuREKA service. The announced environment links CPUs, GPUs, simulators, and quantum processors through a CUDA-Q development layer. Participants are also expected from QuantWare, Quantum Intelligence, and the Korea Research Institute of Bioscience and Biotechnology. The public account names molecular simulation, candidate search, and ADMET prediction as possible uses. Those are concrete pharmaceutical tasks, but the source remains an event preview. It provides no methods paper, dataset, benchmark table, candidate molecule, or measured advantage.
Portability can expose what the QPU contributes
The useful feature may be the ability to run one drug-discovery workload across different backends. A common development environment can keep the surrounding classical code visible while a team compares a simulator, GPU, and available QPU. That does not establish better performance. It can make the comparison easier to inspect. Runtime, accuracy, resource use, variance, and sensitivity to hardware noise all become part of the result. Pharmaceutical researchers can then ask whether the quantum step improves a defined endpoint or only changes the route used to compute it.
The pharmaceutical result is still open
ADMET covers how a drug is absorbed and distributed, how it is metabolized and excreted, and whether it is toxic. Each property depends on different data and validation methods. SDT's preview does not yet name an endpoint, baseline, or test set. Quentir therefore records two separate steps: SDT has described a multi-backend architecture, and KPBMA has created a pharmaceutical forum for it. Readiness for the announced applications remains unranked until a reported experiment shows what ran on the QPU, what stayed classical, and how the output compared with a strong existing method.
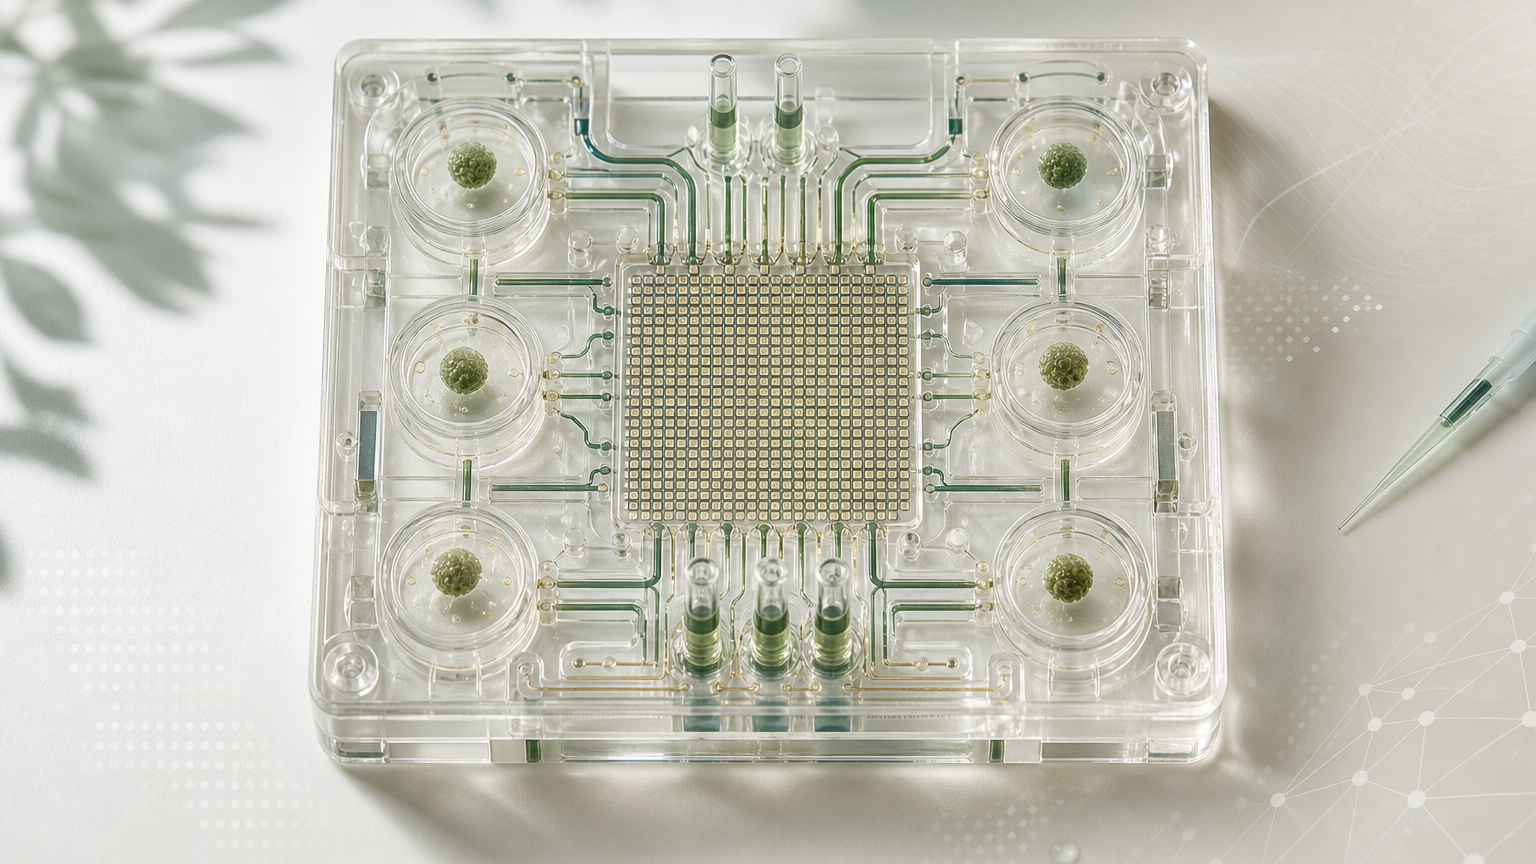
Australia Funds a Quantum Window Into Living Brain Tissue
The project begins before the clinic
Australia has awarded AUD 2.1 million to a University of Melbourne consortium developing a brain-on-chip platform for neurological drug research. The partners are Chromos Labs, Tessara Therapeutics, Quantum Brilliance, and Axol Biosciences. Their stated plan joins human neural micro-tissue to quantum tools that measure electrical activity in real time. The target is preclinical work: observing how laboratory-grown neural tissue responds to candidate therapies before a claim reaches patients. The University announcement names Alzheimer’s disease, schizophrenia, epilepsy, and anxiety disorders as intended fields of use. A later Team France Export account repeats that list and explicitly credits the University source. The disease names describe ambition, not validation. The public record reports a funded development program and no integrated-system result or clinical study.
Electrical behavior can reveal what a final endpoint misses
Neurons communicate through changing electrical states. Continuous measurement can show when a tissue model responds, how long the response lasts, and whether activity returns to baseline. That makes the platform relevant to preclinical drug discovery, where an earlier rejection of a weak candidate can save years of work and reduce the chance that patients enter a trial built on a fragile signal. The benefit depends on control. Tissue batches vary, microfluidic conditions drift, and sensitive electronics can mistake ordinary noise for a drug effect. A useful platform will need blinded comparisons, repeatable preparation, reference measurements, and a clear path from raw signals to the claimed biological response.
The quantum component still needs a technical record
The project accounts describe quantum technology as part of the real-time measurement layer. They do not disclose the sensor architecture, detection limits, noise floor, calibration method, or comparison instrument. That keeps the readiness answer open. Quentir classifies the function as quantum sensing while withholding a numbered readiness level from a grant announcement with no reported integrated result. The next credible milestone is an assembled laboratory system tested on human neural micro-tissue, with controls that distinguish a drug response from sensor noise, tissue variability, and software choices. If that milestone lands, the project may become a better filter for neurological drug pipelines long before it becomes anything a patient or hospital encounters directly.

What the Word Quantum Means on a Hospital CT Scanner
The label describes a detector
Siemens Healthineers has introduced a second generation of its photon-counting CT family in Vietnam. The NAEOTOM Alpha Class is a commercial imaging platform for hospitals, with versions aimed at routine imaging, cardiology, and tertiary or specialist centers. The word quantum points to the detector's handling of discrete X-ray photons. No qubits run a computation inside the gantry. Tiền Phong reports that all three models offer 0.2 millimeter ultra-high-resolution slices and multi-energy data. Alpha.Pro and Alpha.Peak reach temporal resolution down to 66 milliseconds, while Alpha.Peak reaches a reported scan speed of up to 737 millimeters per second.
One platform now serves three clinical settings
The product segmentation turns a physics story into a hospital procurement question. A routine radiology department, a cardiac service, and a tertiary referral center carry different case mixes, motion problems, staffing needs, and service expectations. The same detector principle can therefore produce different value across institutions. Configuration-specific comparisons remain essential: image quality for the intended examinations, radiation dose, contrast use, reconstruction performance, throughput, training, uptime, and the clinical decisions influenced by spectral information. The launch also included SOMATOM On.site, a separate mobile head-and-neck CT system. Its presence makes the distinction useful. One device changes the detector architecture; the other changes where imaging reaches a critically ill patient.
The technology is already in clinical use
Siemens says the first NAEOTOM Alpha entered clinical use in 2021. The company describes its detector as directly converting X-rays into electrical signals while measuring each photon's energy, making spectral information available with every scan. That places the underlying sensing technology at TRL 9 on the shared readiness ladder. Commercial maturity still leaves a local buying question. Hospitals need to establish which model and protocols fit their patients, clinicians, facilities, and budgets. Precise language helps: photon-counting CT is an advanced diagnostic-imaging technology grounded in quantum physics, and its performance belongs in ordinary clinical and operational comparisons.
Madrid Is Buying a Quantum Computer for Hospitals to Share
Madrid has funded a shared quantum machine
The Comunidad de Madrid plans to buy a public quantum computer, install it at the Universidad Politécnica de Madrid, and make it available to universities, research centers, hospitals, companies, and technology startups. The regional government says the system will be delivered in 2029, with about EUR 2 million allocated through that year. Hospitals are explicitly inside the intended user community. The announcement is less specific about what they will do with the machine. It names no vendor, architecture, qubit count, medical project, clinical partner, performance result, or data pathway. Madrid has therefore made a concrete infrastructure commitment while leaving the medical program open.
Hospital access arrives before clinical utility
The phrase hospital access matters because it gives clinical and biomedical institutions a place in the future regional quantum community. Access does not establish a hospital deployment or a validated healthcare use. Medical relevance could eventually emerge through molecular simulation, optimization, biomedical analysis, or another problem that researchers have not yet formulated. Any such project will also inherit healthcare's demands for sensitive-data control, reproducibility, clinical accountability, and continuity of support. A public machine may reduce one barrier to experimentation. It cannot supply the missing use case, classical comparator, or validation path.
The service around the machine will decide its value
Computerworld Spain places Madrid beside existing quantum infrastructure in Barcelona, the Basque Country, and Galicia. Madrid's distinctive claim is regional public ownership. That choice creates a scientific commons whose future rules will shape which projects receive time and support. The useful comparison is a shared imaging or genomics facility: the apparatus matters, while skilled intermediaries make it usable. By 2029, the machine's presence will be easy to verify. More informative outcomes will include whether hospital teams used it, whether projects had strong classical comparisons, whether negative results remained available, and whether public ownership widened participation. Madrid has bought time to build that institution. The first medical contribution may be a clearer map of where quantum computing helps, where it does not, and what a credible next experiment requires.
Inside the 156-Qubit Enzyme Calculation
QC Ware reports a molecular calculation on quantum hardware
QC Ware says it calculated the electrostatic interaction energy of nitric oxide reductase by combining GPU-accelerated molecular modeling, classical chemistry methods, and quantum measurements on IBM's 156-qubit Heron processor. The enzyme is chemically demanding because its active region contains metal. The public announcement makes the electrostatic interaction energy calculation concrete, but it does not disclose the molecular partition, circuit design, measurement count, error mitigation, reference value, or final numerical error. The release therefore supports a precise statement: QC Ware reports that a medically relevant class of molecular calculation reached named quantum hardware. It does not yet show that the quantum step improved the result.
The architecture has a clear division of labor
The hybrid chemistry workflow combines Promethium, GPU-accelerated molecular modeling, classical chemistry methods, and quantum measurements. The release does not disclose how work was partitioned among them. IBM's published description of Heron and System Two provides useful architectural context: its quantum processors operate with classical runtime servers and methods that divide larger calculations. The QC Ware release is the source for the later 156-qubit hardware claim. It also says the demonstration is not currently an integrated Promethium product capability. That sentence prevents a hardware claim from being mistaken for a production service.
The missing benchmark defines the next milestone
The announcement reports no quantum advantage and offers no comparison against a strong classical workflow for the same chemical task. Qubit count cannot supply that missing result. A buyer would need comparative accuracy, resources, runtime, repeatability, and a decision consequence for chemists. The public record therefore places the work at TRL 3: a vendor-reported hardware proof of concept for one molecular property. Its product boundary is commercially informative because it separates an experimental module from the platform available today. The next persuasive record would show what the quantum measurements add at a fixed cost or error, and whether that contribution changes a research decision.

The Same Kind of AI Explanation Split the Room
One interface, two kinds of reader
A Nature Medicine study tested four forms of AI assistance in dermatology with 623 lay participants and 153 primary care physicians. The two groups completed different diagnostic tasks, yet the pattern across the experiments was clear: help from a strong model could improve average performance while exposing the most deferential users to larger errors when the model was wrong. For non-experts, a fluent LLM rationale carried particular force. They trusted the language whether the diagnosis was right or wrong, and vague or generic accounts could feel especially convincing. The result turns automation bias into an interface problem, not only a user-training problem.
The order of the screens changed the behavior
Participants were also assigned to different sequences. Some formed an initial diagnosis before seeing the model's suggestion; others received AI assistance before making their decision. The human-first workflow preserved more room for independent reasoning, while AI-first presentation produced stronger anchoring. Clinicians were more resilient to incorrect advice and gained the least diagnostic accuracy from LLM explanations, although prose could help their confidence track accuracy. The study therefore separates explanation quality from explanation placement. A sound model and readable rationale can still have a different effect when the model speaks first.
Why this belongs in hospital technology review
FDA, Health Canada, and MHRA principles already say that transparency for machine-learning medical devices depends on the audience, context, media, timing, and communication strategy. This study gives explanation timing a concrete clinical meaning. A hospital buys more than an algorithm: it adopts a sequence in which a nurse, physician, specialist, or patient encounters the output. The experiments do not prove that any named commercial product is unsafe, and they do not cover every care setting. They do show that an average accuracy gain can hide a failure mode concentrated among people with the least independent knowledge. No quantum technology was tested. The lesson will still matter if future quantum-assisted systems make medical models faster or more capable, because computation alone cannot decide when a human should see the answer.

The Helmet That Brings Brain Mapping Closer to Childhood
A scanner that moves with the patient
In a Wellcome impact story, Liberty can talk and move while a latticework helmet records the magnetic fields made by her brain. The seventeen-year-old is living with epilepsy, and Wellcome reports that her earlier diagnostic path included ten days in a hospital bed with electrodes placed directly on the brain. The helmet is an optically pumped magnetometer magnetoencephalography system, or OPM-MEG: a wearable brain scanner built around quantum sensors small enough to sit close to the scalp. That proximity matters for children, whose heads sit farther from the fixed detectors in conventional MEG equipment and whose movement can blur a scan.
The clinical comparison has arrived
A prospective Epilepsia study enrolled 68 people with refractory epilepsy for ninety-minute OPM-MEG recordings. The magnetic localization agreed with the epileptogenic zone defined by invasive intracranial recordings in 90 percent of the reported comparisons. Among 51 people who later underwent resection or thermocoagulation, sensitivity ranged from 73 to 85.7 percent depending on the outcome scale, while specificity remained near 65 percent. Those numbers make presurgical epilepsy mapping a clinically consequential use of wearable quantum magnetometry in the records reviewed here. They also keep the claim bounded: the system can contribute useful localization without carrying a surgical decision alone.
A pediatric clinic tests a different constraint
Wellcome reports that the United Kingdom's first dedicated pediatric OPM-MEG clinic is operating at Young Epilepsy with Great Ormond Street Hospital. The technology can fit smaller heads and tolerate more natural movement, bringing magnetic brain mapping into a setting where a rigid adult-sized scanner is especially difficult. The system still needs a shielded room, trained operators, calibration, broader multi-center validation, and regulatory qualification before ordinary hospital use. Its humane promise lies in time: earlier usable maps may shorten part of a long presurgical journey during years when seizures can disrupt development, education, and family life.

A 90-Degree Antenna for a Difficult Organ
The eye makes 7-tesla MRI work hard
The human eye is small, moves easily, and sits among tissues that respond differently to a strong radiofrequency field. Higher magnetic fields can reveal finer anatomy, but they can also create shading, signal voids, and local heating. A team in Berlin and Rostock built a metamaterial antenna around that problem. The printed circuit board bends through 90 degrees over the eyes. Forty subwavelength copper cells are integrated with a two-channel transmit-and-receive loop to reshape the field at the operating frequency of a 7-tesla scanner.
The prototype reached human imaging
The antenna was tested in phantoms, five healthy adults, and one person with treated retinal disease. Three healthy volunteers received direct comparisons with a matched conventional loop. The new design increased transmit efficiency and received signal across the reported eye measurements. A flat version also extended coverage across the occipital region in two healthy volunteers. Safety work combined electromagnetic simulation, human voxel models, magnetic-resonance thermometry, and fiber-optic temperature probes. These results make the device a serious ocular MRI prototype, while the small cohort and technical endpoints stop well short of diagnostic superiority or routine care.
The quantum boundary matters
MRI reads signals produced by nuclear spin and magnetic resonance, placing this work in the quantum-sensing pillar. The metamaterial itself is an engineered radiofrequency structure rather than a quantum computer or algorithm. A contemporary UC San Diego account describes a separate line of quantum metamaterials built from nanoscale quantum elements and notes the broader use of metamaterials to shape MRI fields. The two research lines meet at materials control, but they should not be treated as the same mechanism. For hospitals, the relevant questions remain attached to the actual device: field uniformity, heating, scan performance, reproducibility, patient comfort, qualification, and whether better signal changes a clinical decision.

The Sleep Study Still Has More to Say
A whole night becomes a few summary measures
An overnight sleep study records brain waves, eye movements, muscle tone, breathing, oxygen levels, heart rhythm and body position. Clinical interpretation often compresses that dense sleep physiology into familiar measures such as the apnea–hypopnea index. A Cleveland Clinic registry began with 10,000 studies. Preprocessing retained 9,608 for clustering, and 9,203 studies trained the foundation model. It identified five risk groups with different trajectories for mortality, cardiovascular disease and neurological disease. The highest-risk group had more than twice the mortality risk of the lowest group, while conventional apnea severity categories showed limited prognostic value.
The result survived a second cohort
The researchers tested the framework in the independent Sleep Heart Health Study, a population-based cohort collected with lower-resolution data. The model still distinguished higher- and lower-risk patients. That strengthens the result, but the analysis remains retrospective. It links physiological patterns to later outcomes and does not show that giving clinicians a risk group improves referral, monitoring, treatment or survival. The paper calls for replication in additional cohorts and prospective clinical trials before implementation.
The partnership includes quantum; this study does not
The team came together through the Cleveland Clinic–IBM Discovery Accelerator, a ten-year life-sciences partnership covering AI and quantum computing. IBM Research scientists are among the authors, and the Discovery Accelerator and the National Heart, Lung, and Blood Institute supported the research. This paper used classical artificial intelligence. No quantum computer, sensor, simulation or network appears in the method.
The hospital opportunity lies in data already collected. American sleep laboratories perform an estimated one million to four million studies each year. A reliable secondary analysis could extract more value from the same difficult night without adding another test. Adoption would still require cross-hospital validation, interpretable group definitions, clear consent and data-reuse rules, and a defined clinical response. The model has shown that the sleep study contains more prognostic structure than one familiar score preserves. Medicine has not yet shown how that extra message should change care.
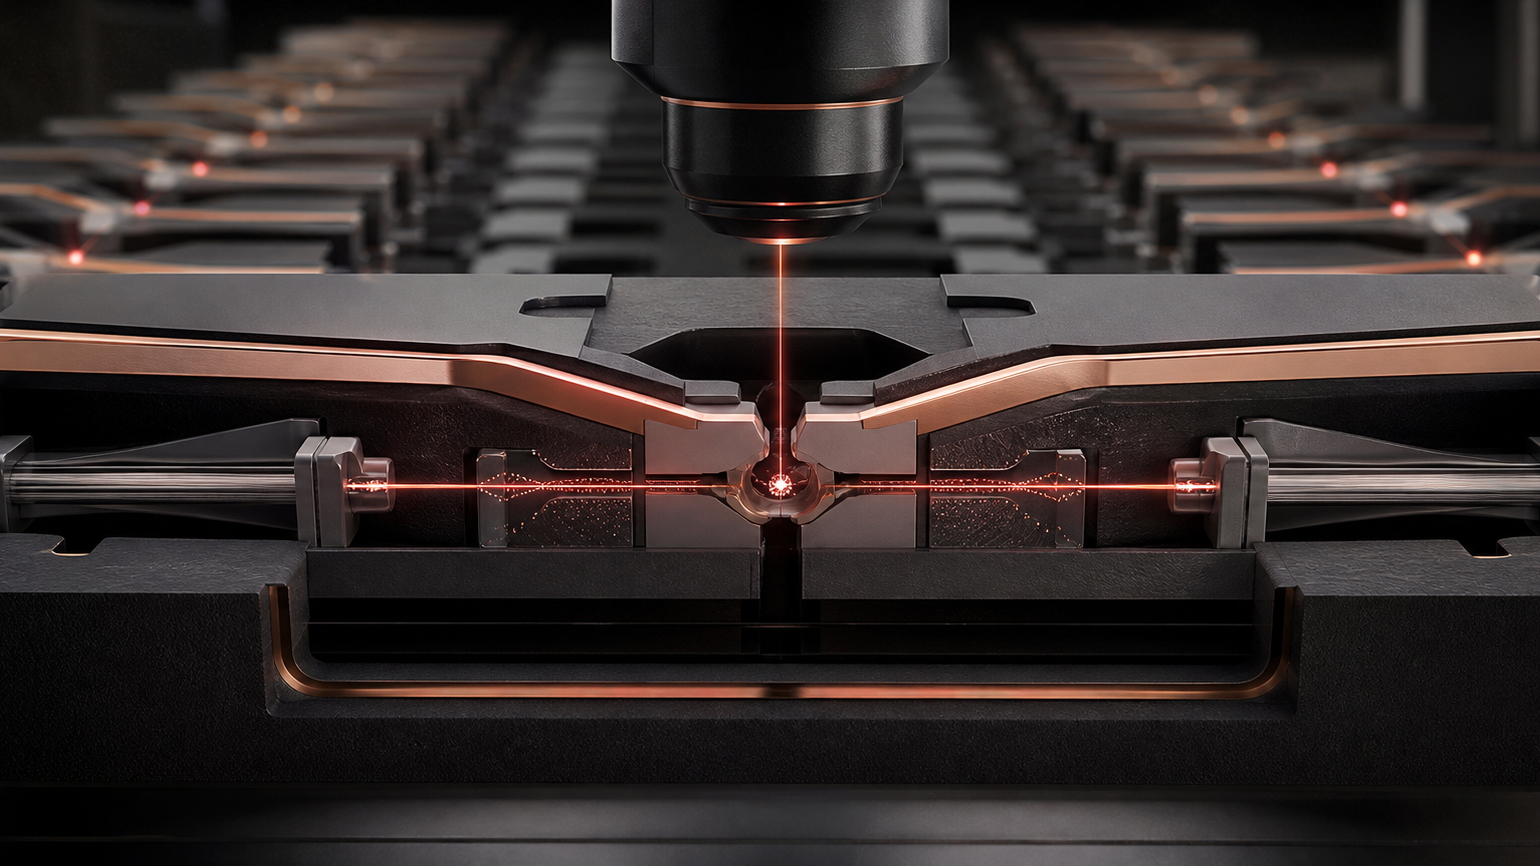
The Quiet Defect Inside a Noisy Diamond
A diamond defect can have a cleaner optical voice
At room temperature, vibrations in a diamond lattice usually disturb the light emitted by an atom-sized defect. A research team led from the University of Illinois has reported a newly identified IL1 color center in nanodiamonds that behaves differently. The peer-reviewed paper describes single-photon emission with linewidths down to 0.3 nanometers at room temperature and brightness above 10 million counts per second at saturation. The usual broad phonon sideband was almost entirely suppressed. Instead, the emitter coupled mainly to one localized vibrational mode outside the diamond phonon band.
The result changes one engineering constraint
That combination matters because many solid-state quantum emitters pay a heavy thermal price for optical coherence. The IL1 result shows room-temperature emission from a real material under laboratory measurement. It does not yet show a complete sensor. The paper reports no controlled spin state, stable charge protocol, integrated readout package, biological sample, analyte, patient cohort, or clinical task. The authors themselves identify spin and charge control, quantum memory, and engineered versions of the defect as future questions.
Medicine enters through the temperature budget
Medical sensing often has to meet living tissue, routine laboratory workflows, or compact instruments at ordinary temperatures. A quantum component that preserves a narrow optical signal without deep cooling could eventually reduce one obstacle between materials physics and a usable device. Sensitivity, selectivity, calibration, biocompatibility, fabrication yield, and reproducibility remain separate problems.
Quentir reads IL1 as an experimental materials result with a credible sensing path and a still-open medical case. Its value today is precise: the team found an unusual way for an emitter to remain optically clean while the surrounding crystal vibrates. The next useful milestones are an integrated sensor, a defined target, comparison with existing diamond defects, and testing in the kind of sample the intended medical job actually involves.

What Happens When Medical AI Receives Conflicting Sources?
A direct answer can still rest on unstable ground
When a language model receives conflicting context on a health question, its answer can become less reliable than an answer drawn from its internal knowledge alone. That is the central result of the HealthContradict benchmark: 920 expert-verified instances pairing one health question and factual answer with two long documents that take opposing positions. Across the tested open models, mixed context reduced accuracy. The strongest biomedical model resisted the effect better than its general-purpose counterpart, but it did not escape it.
The source can change the answer
The more revealing comparison is not model against model. It is the same model under different source conditions. Give the strongest open biomedical system in the main comparison the correct document and accuracy rose to 91.1 percent. Give it only the incorrect document and performance fell by 21.6 percentage points from its no-context control. Give it both sides and accuracy still declined. In one smaller biomedical model, changing which document appeared later shifted accuracy by 5.9 points.
These are controlled benchmark results, not a clinical deployment trial. The core model suite ranged from 1 billion to 8 billion parameters, with additional GPT-4.1-mini and GPT-4o evaluations reported by the authors. The study did not test live retrieval pipelines, clinician use, or patient outcomes. Yet the experiment isolates a practical hazard: retrieving relevant material is not enough when the retrieved material disagrees.
A safer evaluation asks whether disagreement survives synthesis
Medical knowledge is not a static answer key. Studies differ by population, design, endpoint, and date; later work can challenge highly cited findings. A useful clinical AI therefore needs more than citation accuracy. It needs tests that preserve source order, provenance, study design, and the fact of disagreement itself.
For buyers and governance teams, the next benchmark should include source-order permutations, deliberately incorrect context, mixed-quality material, and an escalation path for unresolved conflict. The important question is not whether a model can produce one fluent answer. It is whether the model and the workflow around it can show why the source base does not yet support only one.

Forty-Six Qubits, One Small Cancer Dataset
What the 46-qubit result did
A cancer neoantigen may differ from an ordinary human peptide by one amino acid. The peptide must bind to a patient’s HLA molecule and then be recognized by a T cell. A Science Advances team used quantum convolutional neural networks to model those two filters and combined them in Q-CHIPP.
The largest hardware experiment represented a full nine-amino-acid peptide with 46 qubits. It used 150 training peptides and 50 test peptides, with 20,000 shots per circuit and two noise-mitigation methods. The model reached F1 0.70. The paper’s unrestricted classical network scored 0.65 and its random forest 0.66 on larger training and test splits.
The biological task is harder than binding
A peptide that binds to HLA may still provoke no T-cell response. Q-CHIPP therefore combines a binding model with an immunogenicity model trained only on confirmed binders. This design addresses a known confound: mixing binders and nonbinders can make binding performance look like immunogenicity prediction.
The patient result remains retrospective
The researchers applied Q-CHIPP to 209,889 candidate peptides from 111 people with HLA-A*02:01-positive lung cancer treated with immunotherapy. Predicted antigen burden was associated with overall survival, but the candidate peptides were not experimentally screened for immunogenicity. The study supports external biological testing, not prospective prediction for a new patient.

The Liver Biopsy’s Unmeasured Chemistry
The project starts with a real clinical gap
A liver biopsy can show fibrosis, inflammation and tissue architecture. It still leaves a harder question for the years ahead: which person’s disease will accelerate? A University of Nottingham team now plans to look inside the same type of specimen for a different layer of information: the magnetic signatures associated with reactive oxygen species, measured through defects in microscopic diamond particles.
The university’s July 30 announcement says the NIHR-funded project will aim to measure reactive oxygen species in routine liver biopsy samples. The proposed sensors are nitrogen-vacancy centers in diamond. The clinical ambition is to learn whether this chemical readout can become a progression signal for chronic liver disease. The release establishes a funded translational project and names its specimen, biological target and intended decision. It reports no patient cohort, completed sensor result, accuracy estimate or prospective outcome test.
Earlier biopsies make the question concrete
In a 2013 Journal of Hepatology study, Aravinthan and colleagues examined 105 biopsies from 70 patients with what the paper then called non-alcohol-related fatty liver disease, alongside 60 controls. Hepatocyte expression of the cell-cycle inhibitor p21 correlated with fibrosis stage and with adverse liver-related outcome. In paired biopsies, changes in p21 expression and nuclear area moved with changes in fibrosis stage. Those results connected features consistent with hepatocyte senescence to disease course. They did not test a diamond sensor or establish reactive oxygen species as a prognostic assay.
The sensor needs a complete proof chain
Reactive oxygen species are diverse and often short-lived. A signal near a diamond particle could reflect several paramagnetic contributors, specimen handling or local tissue conditions. The assay must define the physical quantity it measures, demonstrate repeatability across sensors and operators, and survive variation in fixation, processing, storage and section thickness. Clinical validation comes later: a prespecified sensor measurement must improve prediction beyond fibrosis stage and other established information, then hold up in an external patient population.
A Quantum Clinical-Data Claim Stops Before the Benchmark
The workflow has a recognizable architecture
NeuroThera Labs said on July 29 that it had internally validated a proprietary quantum sampling workflow for continuous clinical and biomedical data. The company describes a hybrid process: continuous distributions are converted into energy-landscape representations, quantum dynamics propose samples, and a classical acceptance step preserves the intended distribution. This resembles a published line of quantum-enhanced Markov chain Monte Carlo research. It is a meaningful architecture claim. The release does not disclose the hardware, number of qubits, dataset, clinical task, circuit depth, runtime, convergence diagnostics, or classical comparator.
Correctness and performance remain separate
An acceptance mechanism can protect the target distribution without showing that a sampler reaches useful regions quickly. The missing benchmark gap covers effective sample size, autocorrelation, mixing time, wall-clock cost, encoding overhead, calibration, and repeated-run stability. A 2023 Nature paper by David Layden and colleagues reported fewer iterations than common classical alternatives on tested Ising-model instances and treated larger-scale speedup as conditional. A 2024 analysis by Alev Orfi and Dries Sels found no speedup for a worst-case unstructured problem in the proposal class they studied. Neither result decides NeuroThera's undisclosed implementation. Together they show why problem structure and comparative testing matter.
The company's own release says the work is preliminary, internally validated, unreviewed, and not independently verified. It also says the platform is a research and analytics tool, not a medical device or diagnostic, and that no quantum advantage is assured. For clinical data, the comparison would also need to show that encoding preserves missingness, correlated variables, rare subgroups, and uncertainty. A faster chain through a distorted distribution would not support the intended analysis. The next useful disclosure would join the hardware run, statistical diagnostics, and preservation of clinically relevant data features in one reproducible comparison. Until then, the announcement is best read as an engineering checkpoint rather than a clinical performance result.